




Many parents are pleased when their 6- or 7-year-old is noticeably taller than peers. However, this may indicate precocious puberty, a condition that can halt growth early and significantly affect emotional and psychological development.
A common parental mistake: waiting for a first period or voice break before seeking treatment
With over 20 years of paediatric experience, Dr Nguyen Thi Ngoc Dung, MSc, Specialist Level II, Deputy Head of the Paediatrics and Neonatal Department at FV Hospital, has observed that many families seek treatment for precocious puberty only after their son’s voice has already broken or their daughter has already had her first period. In reality, these signs indicate that puberty has already progressed to its later stages, and the family has missed the critical window for intervention when treatment is most effective in optimising final adult height.
One typical case was that of a 7-year-old girl from Ho Chi Minh City, brought to FV Hospital after her mother noticed breast development. Examination showed her bone age was equivalent to that of an 8-year, 7-month-old, despite her actual age. Her height was increasing rapidly. She was diagnosed with central precocious puberty.
Dr Ngoc Dung recommended GnRH analogue therapy, an injection that temporarily suppresses hormones driving early puberty, to delay menarche and allow more time for growth. However, the family declined due to concerns about hormonal treatment. Less than two years later, the mother returned, visibly distressed, as her daughter, now 9 years and 1 month old, was menstruating twice a month and persistent fatigue.
“This was a deeply unfortunate situation, as it was entirely preventable. The issue extends beyond early menstruation. At 9, this child’s hormone levels matched those of a 12- or 13-year-old. The mismatch between a young body and elevated hormone levels makes these children highly vulnerable to emotional distress, anxiety, and psychological distress that can be difficult to manage,” Dr Ngoc Dung explained.
According to the Endocrine Society (USA), precocious puberty is defined as breast development before age 8 in girls and testicular enlargement before age 9 in boys. Early on, children may grow rapidly, which parents often see as healthy development. However, the premature rise in sex hormones accelerates skeletal maturation, causing growth plates to fuse early. This leads to an earlier end to growth and a shorter adult height than expected.

The hormonal fluctuations of puberty make children more prone to fatigue and emotional stress. Image: Magnific
Three main causes of idiopathic precocious puberty
According to epidemiological data presented by Dr Nguyen Thi Ngoc Dung, MSc, Specialist Level II, at FV Hospital’s medical symposium on “Multidisciplinary Approaches to Optimising Growth and Comprehensive Development in Children” on July 11, 2026, the age of puberty onset in children has been declining markedly across successive decades worldwide.
Whilst the average age of puberty in girls in the 1960s was 13.2 years, it has now fallen to just 9–10 years. Notably, 80–90% of precocious puberty cases in girls are idiopathic, meaning they occur without identifiable structural brain lesions. Girls are affected about ten times more often than boys.
Research by Dr Nhat Nam, PhD, and colleagues, published in the American Journal of Epidemiology in 2025, documented a significant post-COVID-19 increase in cases. Several contributing factors have been proposed:
- Excessive screen time: Blue light exposure may suppress melatonin secretion, a hormone that naturally inhibits the onset of puberty.
- Obesity and nutritional factors: Children who are inactive or overweight have higher levels of leptin. Leptin acts on the hypothalamus to stimulate premature activation of the hypothalamic-pituitary-gonadal (HPG) axis, triggering early puberty.
- Psychological stress: Stress and anxiety elevate stress hormones, which may indirectly stimulate early activation of the HPG axis.
How is precocious puberty diagnosed?
To diagnose central precocious puberty, clinicians use a combination of clinical examination and targeted investigations, including: assessment of breast tissue development, pubic hair, or testicular size; a hand X-ray to determine bone age; sex hormone blood tests; pelvic/ovarian or testicular ultrasound where indicated, to support diagnosis and identify possible underlying causes.
Research by Dr Nhat Nam, PhD, and colleagues, included in clinical practice guidance by the Korean Society of Pediatric Endocrinology, has shown that pelvic or ovarian ultrasound is a simple, non-invasive, and valuable diagnostic tool in girls. It complements bone age assessment and hormone testing as part of a comprehensive diagnostic pathway.
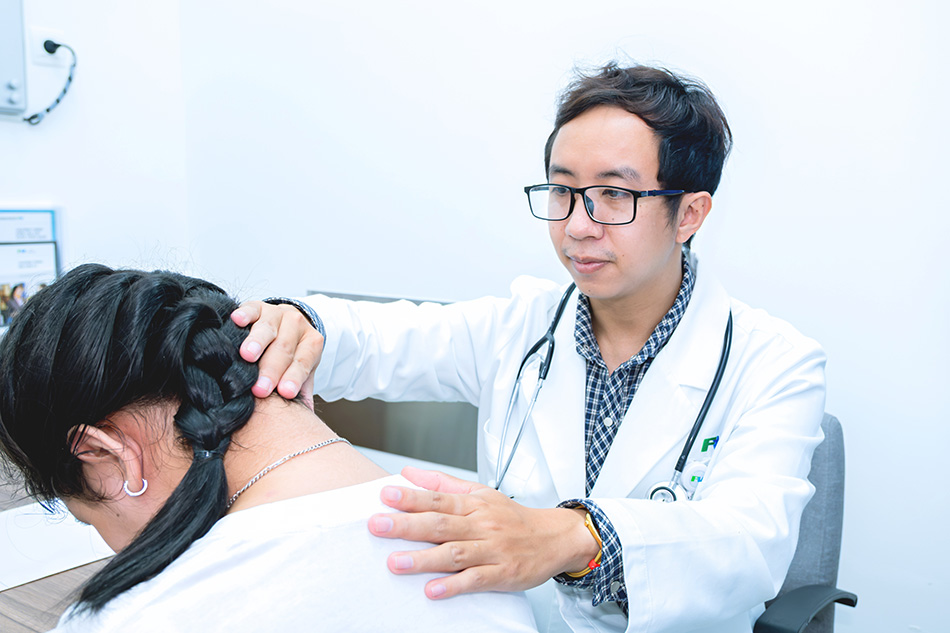
Dr Nguyen Nhat Nam, PhD, paediatric growth disorders specialist
International standard treatment for precocious puberty at FV Hospital
According to the Endocrine Society’s (USA) updated guidelines from June 2026, not every case of precocious puberty requires medication. The decision to treat is fully individualised and based on age of onset, rate of pubertal progression, bone age, predicted adult height, psychological impact and family preferences.
“Children aged 7–8 who show early pubertal signs but progress slowly often require only watchful waiting with review every 4–6 months to avoid unnecessary overtreatment. In contrast, children whose puberty begins before age 7, who have rapid bone age advancement with a significantly reduced predicted adult height, or who experience clear psychological distress will be offered early treatment,” said Dr Ngoc Dung.
When treatment is indicated, children receive GnRH analogue therapy. At FV Hospital, clinicians use a long-acting depot formulation administered by injection every three months, consistent with current international recommendations and replacing the previous monthly regimen. This reduces the number of injections, minimises pain and psychological stress, and significantly improves adherence.
In selected cases, where the predicted adult height is significantly compromised, adjunct growth hormone therapy may be considered alongside GnRH analogue treatment to optimise the child’s final adult height.

Dr Nguyen Thi Ngoc Dung, MSc, Specialist Level II, advises on routine child health monitoring programmes.
At FV Hospital, children with suspected or confirmed precocious puberty are assessed by a multidisciplinary team including a general paediatrician, paediatric endocrinologist, and specialist dietitian. The team develops an individualised monitoring or treatment plan that integrates nutrition, physical activity, and psychological support to optimise overall development.
Dr Ngọc Dung advises parents not to miss the critical window. Observe your child closely, and if you notice unusually rapid height increase, breast tissue development in a girl before age 8, or testicular enlargement in a boy before age 9, seek assessment at a specialist paediatric facility promptly. For consultation and assessment regarding precocious puberty, please contact the Paediatrics Department or the Endocrinology Unit at FV Hospital, 6 Nguyen Luong Bang Street, Tan My Ward (formerly District 7), Ho Chi Minh City. Tel: (028) 3511 3333
Related News
See moreRelated News

Shining star of Aug 2026
The Shining Star of August 2026 has been awarded to Ms Thai Truong Thuy Tien, Liaison Officer. With her dedication and professionalism, Ms Tien continually overcomes challenges and makes valuable contributions to the work of the Liaison Office. Having spent 10 years at FV, Ms Thai Truong Thuy Tien has had a memorable journey filled […]

16th Give Blood – Give Hope blood donation programme: Spreading the spirit of giving
On 25 September 2026, the 16th “Give Blood – Give Hope” blood donation programme, co-organised by FV Hospital and the Blood Transfusion Haematology Hospital, concluded successfully, receiving enthusiastic participation from FV staff, clients and community members. With 134 units of blood collected, the programme helped replenish blood supplies and support emergency care and treatment for […]

Register for ‘afternoon tea with doctors’: Breastfeeding guide & Managing common breast issues
Event Details: – Time: 14:30 – 16:00, Saturday, 24 October 2026 – Location: FV Hospital, 6 Nguyen Luong Bang, Tan My Ward, Ho Chi Minh City Speakers: – Dr Nguyen Thi Thanh Minh, MSc, Specialist Level I, FV Thomson Maternity – Dr Phung Ngoc Thu, Specialist Level I, Head of Breast Care Centre Breastfeeding is […]
Abdominal pain misdiagnosed as digestive issue: 23-year-old woman diagnosed with ovarian torsion
While studying abroad in South Korea, N.T.T.M. (23) experienced unusual pain in her lower right abdomen. She sought treatment at a local hospital and received medication for a suspected digestive issue. After returning to Vietnam to visit her family, the pain recurred and worsened. On her friends’ advice, M. visited FV Hospital for evaluation. She […]
Shining star of Aug 2026
16th Give Blood – Give Hope blood donation programme: Spreading the spirit of giving
Register for ‘afternoon tea with doctors’: Breastfeeding guide & Managing common breast issues

